Dental implants are sometimes covered by insurance, but coverage is rarely straightforward. Most dental insurance plans still classify implants as a major restorative service, which means they may cover only part of the cost, often 30% to 50%, and only after deductibles, waiting periods, and annual maximums are applied. Many plans exclude implants entirely, while others cover the crown but not the implant post or abutment. A common annual maximum for traditional dental insurance is $1,000 to $2,000, which is much lower than the total cost of implant treatment.
A single dental implant in the United States often costs about $3,000 to $6,500 per tooth when the implant post, abutment, crown, imaging, surgery, and follow-up visits are included. If bone grafting or sinus lift procedures are needed, the total can rise by $500 to $3,000 or more. When insurance applies, patients may still pay a large out-of-pocket amount because the plan maximum is reached quickly.
Medical insurance may help in limited situations. This is more likely when tooth loss results from trauma, tumor removal, congenital defects, or medically necessary jaw reconstruction. In those cases, insurers may cover hospital-based portions, imaging, anesthesia, or oral surgery while still excluding the prosthetic tooth replacement itself.
The most useful way to evaluate coverage is to review the policy’s implant wording, annual maximum, missing tooth clause, waiting period, and network rules. A pre-treatment estimate from the dentist and insurer usually provides the clearest answer before treatment begins. If a plan does not cover implants, patients often compare financing, in-house membership plans, health savings accounts, flexible spending accounts, dental schools, and lower-cost alternatives such as bridges or dentures.
Does Dental Insurance Cover Dental Implants
Dental insurance may cover dental implants, but many people are surprised by how limited that coverage can be. In policy language, implants are often placed under major restorative services. That category usually has the lowest reimbursement level in a plan. Preventive services such as cleanings may be covered at 100%, basic services such as fillings at 70% to 80%, and major services such as crowns, bridges, dentures, and implants at 30% to 50%. Some policies list implants by code and offer partial benefits, while others exclude them completely.
Coverage often depends on the specific plan type. Employer-sponsored PPO plans sometimes include implants, while lower-premium plans may not. DHMO plans can reduce fees through a network schedule, though they may not pay a percentage in the same way as PPO insurance. Individual plans bought directly by consumers tend to vary widely. One policy may cover only implant crowns after a 12-month waiting period, while another may cover the surgical implant placement but only up to an annual maximum of $1,500. When the total cost of one implant case reaches $4,500, a $1,500 annual maximum still leaves a large patient balance.
The date of tooth loss can matter. Some insurers use a missing tooth clause, which means they will not cover replacement of a tooth lost before the policy started. This clause is less common than it once was, but it still appears in some plans. Waiting periods are also common. A patient may need to hold the plan for 6 to 12 months before major services become eligible. If treatment starts before the waiting period ends, benefits may be denied.
Network status also affects real cost. A dentist who is in network has agreed to negotiated fees, which can reduce the billed amount by 10% to 30% compared with standard office fees in some regions. Out-of-network coverage may still exist, but reimbursement is often based on the insurer’s allowed amount, not the clinic’s actual fee. That difference can increase your out-of-pocket expense even if the service is technically covered.
For most patients, the practical answer is that dental insurance may help with implants, but it rarely pays the full amount. A detailed benefits check and preauthorization are the most reliable ways to see what the plan will pay before surgery is scheduled.
What Parts of a Dental Implant May Be Covered
Dental implant treatment is made up of several separate services, and insurance may cover some parts while excluding others. This is one reason many patients receive confusing estimates. A complete implant case often includes the consultation, panoramic X-rays or cone beam CT scan, extraction if the tooth is still present, bone grafting if needed, surgical placement of the implant post, healing visits, the abutment, and the final crown. Each of these may be billed under different procedure codes, and insurers may handle them differently.
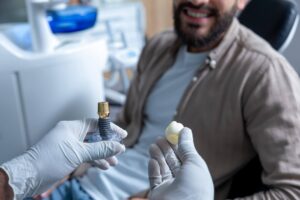
The implant post is the titanium or zirconia fixture placed into the jawbone. Some dental plans specifically exclude this surgical component, even when they cover a crown or denture related to the implant. The abutment, which connects the implant post to the crown, is also often billed separately. Certain plans cover it as part of the implant restoration, while others do not mention it clearly and process it under a general prosthetic code. The implant-supported crown is more commonly covered than the implant post itself, though reimbursement may still be limited to 30% to 50% of the allowed amount.
Diagnostic services may have better coverage than the actual implant. Exams and standard X-rays are commonly covered at 80% to 100% under many dental plans. A cone beam CT scan, which can cost roughly $250 to $600, may be covered in some cases but not all. Extractions are frequently covered as a basic or major service, depending on complexity. Bone grafting is one of the most variable items. A minor graft may cost $300 to $800, while a more extensive ridge preservation or sinus graft can range from $800 to $3,000. Some insurers treat grafting as oral surgery and offer partial coverage; others classify it as implant-related and deny it.
If the treatment involves an implant-supported denture or bridge, coverage may focus more on the prosthesis than on the implants themselves. A plan might cover part of an overdenture but exclude the two to four implants that retain it. In a full-arch case, where four to six implants support a fixed prosthesis, separate line items become even more important because the total fee may reach $15,000 to $30,000 per arch.
Patients benefit from asking for a coded treatment plan. When the office submits each item in advance, the insurer can estimate whether it will pay for imaging, extraction, grafting, sedation, the implant fixture, the abutment, the crown, or only selected portions. That breakdown is usually more valuable than hearing that implants are “covered” in general terms.
When Are Dental Implants Considered Medically Necessary
Dental implants are not automatically considered medically necessary just because a missing tooth affects comfort or appearance. In insurance decisions, medical necessity usually has a narrower meaning. It often refers to treatment required to restore function after trauma, disease, congenital conditions, or major surgery. This distinction matters because standard dental policies may view implants as elective prosthetic replacement, while medical policies may consider coverage when implants are part of reconstructive care.
A common example is facial trauma. If a patient loses one or more teeth in a car accident, workplace injury, sports injury, or assault, implants may be tied to treatment of traumatic damage to the jaw, facial bones, or surrounding soft tissue. Oral and maxillofacial surgeons sometimes document that the implant-supported restoration is necessary to re-establish chewing function, stabilize occlusion, or support reconstructed anatomy. Medical insurers are more likely to review such claims when there is clear injury documentation, imaging, operative reports, and evidence that the tooth loss was directly caused by trauma.
Cancer treatment can also create medically necessary circumstances. Patients who undergo resection of the jaw due to oral cancer may need reconstruction using bone grafts or free flaps. In these cases, implants can help retain prosthetic teeth after removal of part of the maxilla or mandible. A similar argument may apply after treatment for benign but destructive jaw tumors or cysts. Congenital conditions such as ectodermal dysplasia, cleft-related tooth absence, or severe developmental defects may support a medical necessity claim when missing teeth affect speech, nutrition, or craniofacial rehabilitation.
Medical necessity is less likely to be accepted for routine tooth loss from decay, gum disease, or long-term missing teeth, even if implants are the best clinical choice. Insurers may argue that removable dentures or bridges are acceptable lower-cost alternatives. The question is not only whether the implant is beneficial, but whether it is required under the policy’s definition.
Strong documentation improves the chance of approval. This often includes periodontal charting, photographs, CT imaging, pathology reports if relevant, accident reports, physician referrals, and a narrative explaining why simpler alternatives would not restore adequate function. A preauthorization request may take several weeks, and insurers may still deny the claim. Appeals with added documentation sometimes change the outcome. For patients with complex medical or reconstructive needs, the terms “medically necessary” and “covered” are related but not identical, so detailed benefit verification is essential before treatment starts.
How Much Do Dental Implants Cost With and Without Insurance
The cost of dental implants varies by location, provider experience, materials, and how much preparatory treatment is needed. Without insurance, a single dental implant in the United States commonly costs between $3,000 and $6,500. This total often includes the implant post, abutment, crown, surgical placement, routine follow-up visits, and standard imaging. In lower-fee markets, some clinics advertise prices starting near $2,000 to $2,500 for very straightforward cases. In larger metro areas or specialist-led offices with advanced imaging and sedation, totals of $5,000 to $7,000 for one tooth are not unusual.
Preparatory procedures can raise the price. A simple extraction may add about $150 to $500. Surgical extraction can cost $300 to $800 or more. Bone grafting may add $300 to $3,000 depending on the size and complexity of the defect. A sinus lift often ranges from $1,500 to $3,500. Cone beam CT imaging may cost $250 to $600. Sedation, if used, may add several hundred dollars per visit.
With insurance, the patient’s cost depends less on the sticker price and more on three numbers: the coverage percentage, the insurer’s allowed fee, and the annual maximum. If a plan covers implants at 50% but has a $1,500 annual maximum, that maximum may be exhausted during a single treatment phase. For example, if the allowed amount for an implant crown and abutment is $2,400, the plan may pay $1,200. If the implant post is excluded, the patient may still owe $2,000 to $3,500 for the surgery and hardware alone. In another case, if the total fee is $4,800 and the plan covers 50% of all eligible components, the theoretical benefit is $2,400, but a $2,000 annual cap reduces actual payment to $2,000.
Multi-tooth and full-arch cases scale up quickly. An implant-supported bridge replacing several teeth can cost $6,000 to $15,000. Full-mouth implant reconstruction may range from $20,000 to $60,000 or higher depending on the number of implants, prosthetic type, and grafting needs. Insurance contributes more in dollar terms only if the plan has a high annual maximum, staged treatment across benefit years, or an employer plan with implant-friendly prosthetic benefits.
Patients often reduce costs by sequencing treatment over two calendar years, using an HSA or FSA, choosing in-network providers, and requesting a written estimate with procedure codes. That approach gives a clearer picture of the true price with and without insurance.
Does Medical Insurance Ever Cover Dental Implants
Medical insurance can cover dental-implant-related care, but this happens in a narrower set of situations than many people expect. Standard health plans generally do not cover routine tooth replacement when the reason for tooth loss is decay, periodontal disease, or ordinary wear. Those situations are usually treated as dental matters. Medical insurance becomes relevant when the implant is part of treatment for trauma, disease, congenital abnormalities, or reconstructive surgery involving the jaw or face.
A patient injured in a car crash may need emergency surgery, imaging, fracture stabilization, and restoration of missing teeth caused by the accident. Medical insurance may cover the hospital fee, surgeon fee, anesthesia, CT scans, and some reconstructive procedures. Whether the implant post or final prosthetic crown is covered depends on the policy language and on how directly the implant is tied to reconstruction of function. Similar logic can apply after removal of oral tumors, jaw cysts, or portions of bone affected by infection or pathology. If a surgeon documents that implants are necessary to support a prosthesis after resection, the medical plan may review the claim under reconstructive or surgical benefits.
Coverage under medical insurance often works best when billing is divided correctly. The hospital or surgery center may bill facility costs. The oral surgeon or maxillofacial surgeon bills surgical codes. The restorative dentist may bill separately for prosthetic components that a medical plan may not accept. In many cases, medical insurance pays some related expenses while the actual implant restoration remains a dental expense. For example, a health plan may pay for trauma surgery and bone graft reconstruction but deny the crown or abutment as dental prosthetics.
Documentation is critical. Insurers often require accident reports, physician referrals, diagnostic imaging, operative notes, pathology records, and a narrative letter explaining functional impairment. Preauthorization may take 2 to 6 weeks depending on the insurer and complexity of the case. Even when a claim is approved, deductibles and coinsurance under medical insurance still apply. A patient with a $2,000 deductible and 20% coinsurance may still owe substantial costs.
Dual submission is sometimes useful. A clinic may bill the medical insurer for trauma-related surgical care and the dental insurer for prosthetic restoration. Coordination of benefits can be complex, so patients benefit from asking in advance which office staff handle medical-dental crossover claims and whether they have experience documenting medically related implant cases.
How to Check if Your Insurance Covers Dental Implants
Checking implant coverage properly takes more than reading the one-line summary on an insurance card. The most reliable method combines your policy documents, a direct call to the insurer, and a written pre-treatment estimate from the dental office. That process can prevent large billing surprises because implant cases often involve multiple procedure codes billed over several months.
Start by locating the plan’s evidence of coverage or benefits booklet. Search for terms such as “implant,” “endosteal implant,” “abutment,” “implant crown,” “prosthodontics,” “major services,” “missing tooth clause,” and “annual maximum.” If the document says implants are excluded, ask whether related services such as extractions, grafting, or crowns are still covered. If the plan says implants are covered, note the reimbursement level, waiting period, age limits if any, and whether coverage applies only in network.
When you call the insurer, have your member ID ready and ask very specific questions. General questions often lead to vague answers. Useful questions include:
-
Are dental implants covered under my plan, and under which procedure codes?
-
What percentage is covered for the implant post, abutment, and crown?
-
Is there a waiting period for major services?
-
What is my annual maximum, and how much remains this year?
-
Is there a missing tooth exclusion?
-
Do out-of-network benefits apply?
-
Will bone grafting, CT imaging, or sedation be covered?
Ask the representative for a reference number for the call. That record can help if there is a later dispute, though phone statements are not a guarantee of payment. The next step is the most important one: ask the dental office to submit a preauthorization or predetermination with full procedure codes and a treatment narrative. Many insurers respond within 2 to 4 weeks. The estimate usually shows the allowed amount, expected insurance payment, and patient portion.
Check timing as well. If your annual maximum resets on January 1, staged treatment can matter. The extraction and implant placement may occur in one benefit year, while the abutment and crown are completed in the next. Spreading treatment across two benefit periods can sometimes increase total reimbursement by $1,000 to $3,000, depending on the plan. Careful verification is the practical step that turns a rough guess into a predictable financial plan.
Alternatives if Insurance Does Not Cover Dental Implants
When insurance does not cover dental implants, patients still have several realistic options. The right choice depends on budget, oral health, the number of missing teeth, and long-term priorities such as stability, chewing comfort, and bone preservation. Some alternatives are lower-cost tooth replacement methods, while others are ways to make implants more affordable without full insurance reimbursement.
A traditional dental bridge is one of the most common alternatives for replacing a single missing tooth. It usually costs about $2,000 to $5,000 for a three-unit bridge, depending on materials and location. Many dental plans cover bridges more readily than implants because they have been part of standard dental benefits for decades. The tradeoff is that a bridge usually requires reshaping the neighboring teeth for crowns, which may not be ideal if those teeth are healthy.
A removable partial denture is often the least expensive option for replacing one or more teeth. Fees commonly range from $700 to $2,500. For full-arch tooth loss, complete dentures may cost around $1,000 to $3,000 per arch, with premium versions costing more. Many plans cover dentures at a higher predictability level than implants, though coverage percentages and waiting periods still apply. Removable options restore appearance and some function, but they generally provide less stability than implants and may require periodic relines or remakes.
Patients who still prefer implants often reduce costs through financing or staged treatment. Monthly payment plans from third-party lenders or in-house financing can spread a $4,500 implant case over 12 to 60 months. Depending on credit terms, payments may range from about $100 to $450 per month. Health savings accounts and flexible spending accounts are useful because implant treatment is usually an eligible expense, allowing payment with pre-tax funds. For someone in a combined 22% tax bracket, using pre-tax dollars on a $4,000 treatment could produce savings of roughly $880.
Dental schools and residency clinics can also lower costs. Fees may be 20% to 50% below private-practice rates, though treatment may take longer due to teaching schedules and case reviews. Some nonprofit clinics and local assistance programs offer reduced fees for qualifying patients, though availability is inconsistent by region.
If cost is the main barrier, ask the clinic for a phased plan. A patient might have the extraction and graft now, place the implant months later, and complete the crown after the next insurance year or after additional savings are available. That approach does not make treatment cheap, but it can make it manageable without abandoning care.
Are There Waiting Periods, Annual Maximums, or Exclusions
Yes, dental implant coverage is often limited by waiting periods, annual maximums, and specific exclusions. These plan features have a major effect on what insurance actually pays. A policy may technically “cover implants,” yet still provide far less help than patients expect once all restrictions are applied.
Waiting periods are common on major services. A new policy may require you to wait 6, 12, or even 18 months before implant-related benefits become active. Employer plans sometimes waive waiting periods for new hires if the group contract allows it, while individual plans purchased directly by consumers are more likely to enforce them. If implant surgery takes place before the waiting period ends, that phase may not be covered even if the crown is placed later when benefits are active.
Annual maximums are one of the biggest limiting factors. Many dental plans still cap yearly benefits at $1,000, $1,500, or $2,000. Higher-end plans may offer $2,500 to $5,000, though those are less common and often come with higher premiums. Since one implant case can cost $4,000 to $6,000, a patient can hit the annual maximum quickly. That means a plan covering 50% may still stop paying after a small portion of treatment. Some clinics strategically schedule surgery and restoration across two benefit years so a patient can use two annual maximums instead of one.
Exclusions vary widely. Common exclusions include implants themselves, cosmetic procedures, replacement of teeth lost before the policy effective date, and services judged not dentally necessary under the plan. Some policies exclude bone grafting if it is performed solely to support an implant. Others limit replacement frequency, such as one crown every 5 to 7 years or one denture every 5 years. A policy may also require in-network treatment for full benefits.
Frequency limitations and alternate benefit clauses can reduce reimbursement. An alternate benefit clause allows the insurer to pay for a less expensive service, such as a removable partial denture, instead of the implant requested by the patient and dentist. In practice, that means the insurer may contribute only the amount it would have paid for the lower-cost option.
Reading the fine print matters more than the headline summary. Patients should ask for a benefit breakdown that includes waiting periods, annual maximum remaining, deductible, replacement limitations, missing tooth clause status, and any alternate benefit provisions tied to implants or prosthetic treatment.
Best Dental Insurance Plans for Implants
The best dental insurance plans for implants are usually the ones that combine three features: implant inclusion in the benefit schedule, a short or waived waiting period, and a higher annual maximum. There is no single best plan for every patient because availability changes by state, employer group, and insurer network. The practical goal is to compare plan design rather than relying only on brand recognition.
Plans that help most with implants often cover major services at 40% to 50% after deductible and offer annual maximums of at least $2,000. Some premium plans now advertise maximums closer to $2,500 or even $3,500 in certain markets. If the annual maximum is only $1,000, implant coverage may be technically present but financially modest. A higher monthly premium can be worthwhile if you already know you need oral surgery or prosthetic work within the next 12 to 24 months.
PPO plans are usually easier for implant patients to use because they offer a broader dentist network and some out-of-network flexibility. DHMO plans can reduce fees through contracted pricing, but specialist referrals and service availability may be more restrictive. A plan that covers implants but has very few experienced in-network surgeons in your area may not be the strongest practical choice.
When comparing plans, look closely at these details:
-
Implants listed as covered services rather than excluded services
-
Major service coverage percentage, commonly 30% to 50%

-
Annual maximum, ideally $2,000 or more
-
Waiting period for major services, preferably waived or no more than 6 months
-
Missing tooth clause status
-
Coverage for bone grafting, extractions, and implant crowns
-
Network size for prosthodontists, oral surgeons, and periodontists
It is also worth comparing the insurer’s negotiated fees. A plan with a 50% implant benefit but lower allowed fees may produce a similar patient cost to a 40% plan with stronger contracted pricing. In some cases, the network discount alone saves 10% to 25% before insurance payment is even applied.
For readers choosing between plans during open enrollment, it helps to estimate total yearly value. Add the annual premium cost, expected deductible, and likely patient share, then compare that with the amount the plan may realistically pay for your implant case. A plan is “best” when the math works in your favor and the provider network can actually deliver the treatment you need.
Dental Implants Insurance FAQs
People shopping for implant coverage usually ask the same practical questions because the language in dental insurance policies can be hard to decode. One common question is whether insurance pays for the whole implant. In most cases, no. Plans that include implants often cover only 30% to 50% of eligible charges, and annual maximums such as $1,500 or $2,000 limit total reimbursement. Patients often still pay several thousand dollars out of pocket.
Another frequent question is whether the crown is covered if the implant post is not. That does happen. Some plans exclude the surgical implant fixture but cover the implant crown as a major restorative service. Others may cover the abutment and crown after osseointegration is complete. The only reliable way to know is to review the code-specific predetermination.
Patients also ask whether insurance will cover bone grafting. Sometimes it does, often it does not. A small graft tied to extraction may receive partial coverage under oral surgery or periodontal benefits, while a graft done mainly to support future implant placement may be denied. Fees vary widely, from about $300 for a minor graft to several thousand dollars for extensive reconstruction.
A related question is whether implants are covered when a tooth was lost years ago. Some plans allow this, while others use a missing tooth clause or replacement limitation. If the tooth was missing before the policy effective date, the plan may deny benefits. This is why effective dates matter.
People often wonder if it is worth buying insurance specifically for implants. That depends on timing and plan structure. If a policy has a 12-month waiting period, a $1,500 annual maximum, and a full implant exclusion, it may not help much for near-term treatment. If a plan includes implants at 50%, has no waiting period due to employer enrollment, and offers a $2,500 maximum, it can provide meaningful savings.
One more common question concerns age. There is usually no upper age limit for implant coverage in standard adult plans, but eligibility depends on oral and general health rather than age alone. For older adults, benefits may interact with retiree coverage, Medicare Advantage dental add-ons, or supplemental dental plans.
Insurance for implants is less about a simple yes-or-no answer and more about policy mechanics. Patients who request a written estimate with exact codes tend to make better financial decisions than those relying on verbal summaries alone.
Does Medicare Cover Dental Implants
Original Medicare usually does not cover routine dental care, and that includes most dental implant treatment. Medicare Part A and Part B are focused on hospital and medical services, not standard dental restorations. If a person needs an implant because of ordinary tooth loss, decay, or periodontal disease, Original Medicare generally does not pay for the implant post, abutment, or crown.
There are limited exceptions when dental services are integral to a covered medical procedure. For example, if a patient is hospitalized for treatment of jaw fractures, facial trauma, oral cancer surgery, or another covered condition, Medicare may pay for related hospital-based or medically necessary physician services. In that setting, imaging, surgery, and inpatient care may be covered while the actual replacement tooth restoration may still be excluded. The key difference is whether the dental work is inseparable from medical treatment of a covered disease or injury.
Medicare Advantage plans, also called Part C plans, are different. Many of them include optional dental benefits not found in Original Medicare. These benefits vary sharply by insurer and county. One plan may cover preventive care only, while another may offer comprehensive benefits that include major services such as crowns, dentures, or implants. Even when implants are included, plans often impose annual allowances such as $1,000 to $3,000, copayments, network restrictions, and prior authorization requirements. A full implant case often exceeds these allowances.
For example, a Medicare Advantage plan with a $2,000 yearly dental benefit may contribute meaningfully toward a single implant, but if the total treatment cost is $5,000, the member still faces a substantial balance. Some plans cover only extraction and dentures, not implants. Others cover implants only under a supplemental comprehensive dental rider with an added premium.
Patients on Medicare should not assume that all “dental coverage” includes implants. The smart approach is to review the plan’s evidence of coverage and ask whether implant procedure codes, abutments, bone grafts, and implant crowns are payable services. If the answer is unclear, request a written pre-treatment estimate from the provider.
For many older adults, the real-world payment strategy combines Medicare Advantage dental benefits, supplemental dental insurance if available, HSA funds for those still eligible before Medicare enrollment, and staged treatment planning. That approach is often more realistic than expecting broad implant coverage under Original Medicare alone.
Does Medicaid Cover Dental Implants
Medicaid coverage for dental implants is highly variable because adult dental benefits are largely determined at the state level. That means one state may offer broad adult dental services, while another provides only emergency extractions and pain relief. For children enrolled through Medicaid and CHIP, dental coverage is generally stronger due to federal requirements, but implant coverage is still uncommon unless there is a compelling clinical reason.
In many states, routine adult implant coverage is limited or excluded. State Medicaid programs often prioritize lower-cost tooth replacement options such as removable partial dentures or complete dentures when those services are covered. The program may view implants as a higher-cost alternative rather than the basic standard. This is one reason adults seeking implants through Medicaid often hear that the service is not covered, even when other dental treatment is.
Coverage becomes more possible when there is a documented medical or functional necessity. Examples may include trauma, congenital absence of teeth, severe craniofacial anomalies, tumor-related defects, or post-surgical reconstruction of the jaw. Even then, approval usually requires extensive documentation, specialist evaluation, and preauthorization. The state Medicaid agency or managed care contractor may request X-rays, photographs, physician letters, and a narrative showing why a denture or bridge would not adequately restore function.
Managed Medicaid plans can add another layer of complexity. In some states, dental benefits are administered by contracted plans rather than directly by the state. Network rules, referral pathways, and prior authorization requirements may differ across plans. A patient might need to see a designated oral surgeon or clinic to even begin the approval process.
If you are trying to determine whether Medicaid may help, start with your state’s adult dental benefits handbook or your managed care member services line. Ask for the written policy on implants, oral surgery, bone grafting, and prosthodontics. It is useful to ask whether implants are ever covered, under what criteria, and whether out-of-network specialty referrals are allowed for reconstructive cases.
Even in states with limited implant benefits, Medicaid may still cover related services such as extractions, infection treatment, imaging, or dentures. Patients sometimes combine those covered basics with reduced-fee specialty care, dental school treatment, or financing for the implant portion. The answer under Medicaid is rarely universal, so state-specific verification is essential before treatment is planned.
Does Delta Dental Cover Implants
Delta Dental may cover implants, but coverage depends on the exact plan rather than the brand name alone. Delta Dental operates through state-based member companies and offers many different employer, individual, PPO, and HMO-style plans. One Delta plan may include implants under major restorative benefits, while another excludes them entirely. This is why asking “Does Delta Dental cover implants?” usually leads to the response “It depends on your plan.”
In plans where implants are covered, benefits commonly follow the major-service structure. That often means partial reimbursement, such as 30% to 50% of the allowed fee after deductible. Annual maximums still apply. If your plan has a $1,500 or $2,000 annual cap, a single implant case may use most or all of that benefit. Some Delta plans also apply waiting periods for major services, often 6 to 12 months for newly enrolled members unless the employer group waives them.
Delta plans may cover related services differently from the implant fixture itself. Exams, standard X-rays, and extractions are often easier to get covered than the implant post. In some cases, the crown or prosthetic portion receives coverage while the surgical implant hardware is limited or excluded. Bone grafting may be covered in narrow circumstances or denied as implant-related, depending on the plan language.
Network participation matters with Delta Dental because contracted fees can lower the billed amount. A PPO dentist in network may save the patient money before benefits are even applied. Out-of-network reimbursement can still exist, but payment is usually based on Delta’s allowance schedule, not the office’s full fee. That gap can affect the final out-of-pocket total significantly.
Patients with Delta Dental should request three pieces of information: whether implants are covered, what percentage applies to each code, and how much annual maximum remains. The most reliable path is to have the dental office submit a predetermination with full procedure codes for imaging, extraction, grafting, implant placement, abutment, and crown. Delta then issues an estimate showing expected payment based on current benefits.
Because Delta Dental offers so many plan versions, two patients in the same city may have completely different implant benefits. The plan booklet and pre-treatment estimate matter far more than the insurer’s name by itself.
How to Get Dental Implants Covered by Insurance
Getting dental implants covered by insurance starts with understanding that approval is usually won through documentation, coding, timing, and policy fit rather than through a simple request. Patients cannot force a plan to cover an excluded service, but they can improve the chance of receiving every dollar available under the policy.
The first step is to obtain a detailed written treatment plan. Ask the dental office to separate each service by procedure code: exam, imaging, extraction, grafting, implant placement, abutment, and crown. Insurers process claims by code, not by general descriptions. A coded plan helps identify which pieces may qualify even when the full implant case does not.
Next, ask the office to submit a preauthorization or predetermination before treatment begins. This allows the insurer to review records and estimate benefits. Include supporting X-rays, periodontal findings, intraoral photos, and a clinical narrative. If there is trauma, congenital tooth absence, tumor surgery, or jaw reconstruction, the narrative should clearly state the functional reason the implant is recommended. Strong records matter because insurers often deny vague submissions.
Timing can increase benefits. If your plan has a $2,000 annual maximum, splitting treatment across two benefit years may double the available reimbursement. For example, extraction and implant placement might occur in November, while the abutment and crown are completed after January 1 when benefits reset. The office should confirm that this timing fits the clinical healing period, which is commonly 3 to 6 months for osseointegration.
Use network advantages whenever possible. In-network providers often reduce fees by contract, which can lower your patient share by hundreds of dollars. Review whether your plan has a waiting period, missing tooth clause, or alternate benefit clause. If the tooth was lost before the plan began, ask whether any exception process exists. If the insurer substitutes a bridge or denture benefit, request the exact alternate benefit amount so you can compare options.
If the initial claim is denied, appeal with added documentation. Appeals are stronger when they include a specialist’s letter, chart notes showing functional problems, radiographs, and clarification of why lower-cost options are unsuitable. In medically related cases, ask whether both dental and medical insurance should be billed. Coordination between the surgeon, restorative dentist, and insurer often makes the difference between no benefit and partial payment.
The realistic goal is not usually full coverage. It is to capture every eligible benefit, reduce fees through network contracts, and structure treatment so out-of-pocket costs are as low and predictable as possible.