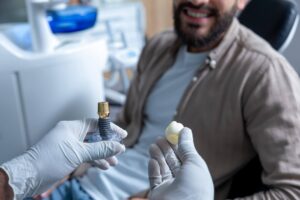
Responsibility for dental implant failure depends on why the implant failed, when the problem appeared, and whether the issue was preventable. A failed implant is not automatically the dentist’s fault. Some implants fail because of surgical error, poor treatment planning, improper placement angle, nerve or sinus complications, or failure to diagnose gum disease or insufficient bone before surgery. In those situations, the treating dentist, oral surgeon, periodontist, or clinic may carry legal and professional responsibility.
Some failures happen for reasons outside the clinician’s control. Dental implants can fail when a patient smokes heavily, misses follow-up visits, does not clean around the implant, ignores signs of infection, or has uncontrolled diabetes that affects healing. Medical conditions such as osteoporosis, severe bruxism, radiation history, or immune disorders can also increase risk even when treatment was technically sound.
Timing matters. Early implant failure often occurs within the first 3 to 6 months, usually before full osseointegration. This phase is commonly linked to infection, overheating of bone during drilling, lack of primary stability, or poor healing conditions. Late implant failure may occur years later and is often associated with peri-implantitis, bone loss, overload from a poorly designed bite, or neglected maintenance.
In practical terms, responsibility is determined by reviewing records such as X-rays, CBCT scans, consent forms, periodontal charting, implant brand details, laboratory work, and follow-up notes. Independent experts often assess whether the provider met the accepted standard of care. If the provider failed to diagnose clear risk factors, used improper technique, or did not inform the patient of known risks and alternatives, liability may be stronger. If the patient failed to follow written care instructions or concealed medical information, responsibility may be shared.
Published long-term studies often report implant survival rates around 90% to 98% over 10 years in suitable candidates, which means failure is uncommon but not rare. When a single implant can cost $3,000 to $6,500 or more in many markets, identifying the true cause of failure becomes medically and financially important.
What Causes Dental Implant Failure
Dental implant failure can happen for many reasons, and the exact cause is often a mix of surgical, biological, mechanical, and patient-related factors. An implant is expected to bond with the jawbone through osseointegration, a process that usually takes 8 to 16 weeks in straightforward cases and longer when bone grafting is involved. If this bond does not form properly, the implant may become mobile, painful, or infected. Early failure tends to appear within the first few months and is often tied to issues during planning or surgery. Late failure may occur after a crown has already functioned for years.
One major cause is infection. Bacterial contamination during surgery or poor oral hygiene after placement can lead to peri-implant mucositis or peri-implantitis. Mucositis affects soft tissue and may be reversible, while peri-implantitis causes bone loss around the implant. Studies often report peri-implantitis prevalence figures ranging from about 10% to over 20% of implant patients depending on definitions and follow-up period. The risk rises in smokers, people with a history of periodontitis, and patients who do not attend maintenance visits every 4 to 6 months.
Insufficient bone quantity or poor bone quality is another common factor. If the jawbone is too thin or soft, the implant may not achieve enough primary stability. In many clinics, insertion torque of roughly 25 to 45 Ncm is considered favorable for initial stability, though exact targets vary by system and case type. Bone grafting or sinus lift procedures may be needed when the implant site is weak or anatomically limited. Skipping that assessment can increase failure risk.
Mechanical overload also matters. If the bite is not adjusted properly, or if the patient grinds their teeth at night, the implant may be exposed to repeated excess force. This can loosen screws, fracture ceramic restorations, or contribute to bone loss over time. Bruxism patients often need a night guard, and in full-arch cases the framework design must distribute forces carefully.
Medical factors can interfere with healing. Uncontrolled diabetes, heavy smoking, some antiresorptive medications, radiation therapy to the jaw, and immune disorders may reduce blood supply or bone remodeling. Smoking more than 10 cigarettes a day is frequently associated with a noticeably higher implant complication rate. Failure can also stem from poor treatment planning, wrong implant size, overheating bone during drilling, poor angulation, or failure to manage gum disease before surgery. In many failed cases, the cause is not one dramatic mistake but a chain of smaller problems that gradually undermine the implant.
Who Can Be Held Liable for a Failed Dental Implant
Liability for a failed dental implant can rest with different parties depending on how the treatment was planned, delivered, and monitored. A failed result alone does not prove negligence. Dental treatment carries known risks, and even a well-placed implant can fail because of biological variables. Liability usually becomes a serious issue when the evidence shows that a provider did not meet the accepted standard of care or when a product defect played a measurable role.
The treating dentist is often the primary focus. This may be a general dentist who places implants, an oral surgeon, or a periodontist. If that professional failed to evaluate bone volume, missed active gum disease, selected the wrong implant dimensions, damaged anatomical structures, placed the implant at an unstable angle, or did not provide proper follow-up, they may be responsible. In some cases, the restorative dentist and the surgeon are different people. One may place the implant while another designs and fits the crown. If the crown creates an excessive bite force or poor hygiene access, the restorative phase may contribute to failure even if surgery was acceptable.
The clinic or dental practice may also be liable. A clinic can be responsible for staffing failures, poor sterilization protocols, inadequate supervision, missing records, defective scheduling of follow-up care, or misleading advertising about success rates. If a clinic promises unrealistic outcomes such as “guaranteed lifetime implants” without appropriate disclaimers, that may affect a legal dispute even when the medical issues are complex.
Dental laboratories can become part of the analysis if they manufacture a prosthesis that does not match the prescription or introduces mechanical stress. This is less common, though poorly fitting components can lead to screw loosening, micromovement, or repeated fracture. Implant manufacturers may be liable in rare cases involving a defective implant fixture, fractured component, contaminated surface, or faulty connection design. Product liability usually requires technical evidence, batch details, and expert review.
Patients themselves can share responsibility. If a patient conceals smoking habits, ignores aftercare instructions, skips hygiene visits for years, continues untreated bruxism, or fails to report infection signs, the case may involve contributory negligence. Legal systems differ by country and state, but shared fault can reduce compensation. Determining liability usually depends on a detailed record review that includes consent forms, radiographs, periodontal history, medical disclosures, treatment notes, and maintenance compliance over time.
Is the Dentist Responsible for Dental Implant Failure
A dentist is not automatically responsible every time a dental implant fails. Implant dentistry has high long-term success rates, often reported around 90% to 98% over 10 years in appropriate candidates, yet failures still occur in routine practice. The key question is whether the dentist acted within the accepted standard of care from diagnosis through follow-up. If the dentist performed a proper medical and dental assessment, informed the patient of realistic risks, used sound surgical technique, and monitored healing appropriately, an unsuccessful outcome may be considered a known complication rather than negligence.
Responsibility becomes more likely when there is evidence of avoidable error. Examples include placing an implant in a site with active infection, failing to order necessary imaging such as a panoramic radiograph or CBCT when anatomy is unclear, ignoring severe bone loss, or placing the implant too close to adjacent roots, the inferior alveolar nerve, or the maxillary sinus. Technical errors can also matter. Overheating bone during drilling, poor primary stability, contamination of the surgical field, or using the wrong implant size may all contribute to early failure. If records show these errors and the implant fails soon after surgery, the dentist’s role may be difficult to defend.
Communication and consent are also part of professional responsibility. A dentist should explain expected healing time, likely costs, alternatives such as bridges or removable dentures, and the patient’s own risk factors. A smoker with untreated periodontitis and poorly controlled diabetes does not have the same prognosis as a healthy non-smoker. If that difference was never discussed, or if the chart lacks informed consent, a complaint or legal claim may be stronger. In many regions, complete consent documentation includes diagnosis, treatment options, risks, benefits, likely complications, and estimated fees, which may range from $3,000 to $6,500 or more for one implant with restoration.
There are also situations where the dentist is only partly responsible or not responsible at all. If a patient refuses a bone graft, declines a night guard despite heavy bruxism, fails to return for review visits, or neglects oral hygiene around the implant, the outcome may reflect shared responsibility. Courts, insurers, and dental boards usually look at the entire timeline rather than one isolated event. The answer depends less on whether the implant failed and more on whether the dentist’s decisions and actions met what a competent provider would reasonably have done in the same situation.
Can Poor Aftercare Cause Dental Implant Failure
Poor aftercare can absolutely cause dental implant failure, and in many delayed failure cases it is one of the main reasons. Once the implant is placed, the body still needs time to integrate the titanium surface with the surrounding bone. That process is vulnerable during the first 6 to 12 weeks, and the long-term health of the implant depends on clean soft tissues, stable bone levels, and controlled biting forces. If aftercare is weak, bacteria can accumulate around the implant collar and trigger inflammation that gradually destroys the supporting bone.
Oral hygiene is central. Unlike a natural tooth, an implant does not have the same periodontal ligament response, so inflammation can spread differently and bone loss can advance with fewer early symptoms. Patients who do not brush effectively twice a day, fail to use interdental brushes or floss designed for implants, and miss professional cleaning visits every 4 to 6 months are more likely to develop peri-implant disease. In a busy clinical setting, our readers often hear that “the implant itself cannot decay,” which is true, but the tissue around it can still break down. Once enough bone is lost, the implant may loosen and require removal.
Smoking is a major aftercare problem. Heavy smokers often heal more slowly because nicotine reduces blood flow and affects tissue repair. Research frequently shows higher failure rates among smokers, with risk increasing further when smoking is combined with poor plaque control or a history of gum disease. Chewing hard foods too early can also interfere with healing. Many clinicians advise soft foods for several days and caution against loading the area until stability is confirmed. If a temporary restoration puts pressure on the implant before osseointegration is mature, micromovement above roughly 50 to 100 microns may disrupt bone healing.
Missed follow-up visits are another issue. Dentists often schedule reviews at 1 to 2 weeks, a few months later, and then at regular maintenance intervals. Those visits help identify loosening screws, bite imbalance, early inflammation, or hygiene problems before they become serious. Poor aftercare also includes ignoring symptoms such as bleeding, persistent bad taste, swelling, or discomfort when chewing. A small problem detected early may be managed with debridement, antiseptic rinses, occlusal adjustment, or antibiotics. Left untreated for months, it can progress to major bone loss. In many real-world cases, aftercare is not just a supportive detail. It is a decisive factor in whether the implant lasts 2 years or 20 years.
What Are the Signs of Dental Implant Failure
The signs of dental implant failure can appear early or late, and some are subtle enough that patients mistake them for normal healing. Mild soreness, slight swelling, or tenderness during the first few days after implant surgery can be expected. Problems arise when symptoms intensify, persist beyond the normal healing period, or return after the area had already settled. One of the clearest warning signs is mobility. A dental implant should feel stable. If the implant fixture itself moves, not just the crown or abutment, that is a serious sign that osseointegration may have failed or that supporting bone has been lost.
Pain is another sign, though it must be interpreted carefully. Temporary discomfort during the first week is common and usually manageable with standard pain relief. Ongoing pain after several weeks, increasing pain while chewing, or deep throbbing discomfort may point to infection, overload, nerve irritation, or implant instability. Bleeding around the implant, swollen gums, redness, and pus discharge can indicate peri-implant mucositis or peri-implantitis. A bad taste, chronic bad breath, or fluid coming from the gum pocket may also suggest bacterial infection.
Changes in function often appear before dramatic pain. A patient may notice that the bite feels “high,” the crown feels loose, or chewing becomes uncomfortable on one side. Sometimes the issue is a loosened abutment screw rather than true implant failure, which is still important because untreated instability can damage the surrounding structures. Bone loss is often visible only on X-rays, which is why periodic radiographic review matters. Some early crestal bone remodeling is expected, but progressive radiographic bone loss combined with bleeding on probing and deepening pockets is concerning.
Numbness, tingling, or altered sensation can occur if the implant is too close to a nerve, though this is more often linked to placement complications than later biological failure. In the upper jaw, sinus symptoms such as pressure or recurrent sinus issues may occur if an implant has encroached on the sinus region. Soft tissue recession around the implant may expose metal threads, making the site more difficult to clean and more prone to inflammation.
Timing gives useful clues. Failure within the first 3 to 6 months often points to poor integration, infection, or early mechanical disturbance. Failure after 2 to 5 years more commonly reflects peri-implantitis, overload, poor maintenance, or prosthetic design issues. Any sign of mobility, persistent swelling, increasing pain, or gum discharge should be evaluated quickly, because early treatment may save the implant or at least reduce the cost and complexity of replacement.
When Is Dental Implant Failure Considered Malpractice
Dental implant failure is considered malpractice when the failure is linked to care that falls below the accepted professional standard and directly harms the patient. Malpractice is not the same thing as an unfavorable result. Even careful, well-documented implant treatment carries known risks such as non-integration, infection, bone loss, sinus issues, and prosthetic complications. A legal claim usually requires more than proof that the implant did not last. It requires evidence that the provider acted unreasonably compared with what a competent dentist or specialist would have done in similar circumstances.
Common malpractice scenarios include poor case selection, inadequate diagnosis, and major planning errors. If a dentist placed an implant without evaluating active periodontal disease, ignored severe bone loss, failed to identify uncontrolled diabetes or other medical risks, or skipped essential imaging in a complex case, those omissions can form the basis of malpractice. Technical errors may also qualify. Examples include damaging the inferior alveolar nerve, perforating into the sinus without proper management, overheating bone during drilling, placing the implant with inadequate stability, or using an implant system in a clearly unsuitable way.
Informed consent is a major legal issue. Patients should be told about treatment alternatives, expected costs, healing timelines, and material risks. If a patient was not warned about the increased failure risk from smoking a pack a day, severe bruxism, or a need for bone grafting, and the chart contains little or no consent documentation, that weakens the defense. In many disputes, poor records create as much trouble as poor treatment. Missing progress notes, absent radiographs, incomplete periodontal charting, and no record of post-operative instructions make it harder to show that care was appropriate.
Causation matters. A patient must usually show that the dentist’s breach caused measurable harm such as implant loss, pain, infection, nerve injury, bone damage, corrective surgery, lost wages, or substantial additional cost. If the patient would likely have had the same outcome because of severe uncontrolled risk factors, malpractice is harder to prove. If expert review shows that a preventable error directly triggered the failure, the case becomes stronger.
Financial losses can be significant. Removing a failed implant, grafting the site, waiting 3 to 6 months for healing, and replacing the implant and crown can cost $4,000 to $10,000 or more, depending on complexity. When that expense flows from substandard care rather than ordinary clinical risk, malpractice analysis becomes much more serious.
How Is Responsibility Determined in Dental Implant Failure Cases
Responsibility in dental implant failure cases is determined by reconstructing the entire course of treatment and comparing it with accepted professional standards. The analysis is rarely based on one photo or one painful symptom. It usually begins with records: consultation notes, health history forms, smoking disclosures, periodontal charting, X-rays, CBCT scans, treatment plans, consent documents, surgical notes, implant brand and size details, torque or stability information, laboratory prescriptions, and follow-up entries. If the records are thin or contradictory, that alone can become important because complete documentation is part of responsible clinical practice.
Experts then look at timing. Failure during the first few weeks or months may suggest poor planning, contamination, insufficient stability, overheating of bone, or premature loading. Failure years later raises different questions such as maintenance quality, peri-implantitis, crown design, bite overload, or patient hygiene. Radiographs are often central because they can show baseline bone levels, implant angulation, proximity to anatomical structures, and progression of bone loss over time. A CBCT scan may reveal whether the site had enough bone at the start or whether the implant was placed in a compromised position.

Standard of care is the core legal concept. This asks what a reasonably competent dentist, oral surgeon, or periodontist would have done under similar conditions. Experts consider whether the provider recognized risk factors such as smoking, diabetes, bruxism, previous periodontitis, thin bone, or parafunctional habits. They also assess whether those risks were discussed and managed. For example, if a patient with uncontrolled diabetes had an HbA1c well above recommended levels and the provider proceeded without coordination or warning, that could weigh heavily. If a heavy bruxism patient was never offered a night guard and the restoration fractured repeatedly before failing, the restorative planning may be scrutinized.
Patient conduct is also reviewed. Courts and insurers may examine missed appointments, neglected cleaning, smoking habits, refusal of bone grafting, refusal of protective appliances, or failure to report symptoms early. In some legal systems, this can reduce or divide compensation under shared-fault rules. Product defects are considered if there is evidence of a fractured fixture, faulty abutment connection, or manufacturing irregularity, though this is less common than treatment-related or maintenance-related causes.
Independent dental experts often prepare written opinions. They may evaluate whether the implant should have been placed at all, whether a bridge or denture would have been safer, and whether the provider’s decisions were within mainstream clinical practice. Responsibility is usually determined not by emotion or disappointment, but by records, imaging, expert comparison, and a clear explanation of cause and effect.
What Should You Do If Your Dental Implant Fails
If your dental implant fails or seems to be failing, the most important step is to get it assessed quickly rather than waiting to see if it settles on its own. A loose implant, swelling, pus, bleeding, increasing pain, or trouble chewing should be examined by the treating dentist or by another implant professional if you have lost confidence in the original provider. Delay can lead to more bone loss, more infection, and a more expensive repair plan. In some cases, early intervention can save the implant or at least preserve enough bone to make replacement simpler.
Start by documenting your symptoms. Note when the pain began, whether the implant or crown feels loose, whether there is bleeding or discharge, and whether chewing makes it worse. Keep photos if swelling or gum changes are visible. Ask for a full clinical exam and updated radiographs, and request copies of your records. These may include pre-treatment X-rays, CBCT scans, consent forms, invoices, surgical notes, implant system details, and maintenance records. If the situation later turns into an insurance dispute or legal claim, complete records matter.
During the dental visit, the provider should determine whether the issue is true implant failure or a repairable complication such as a loose crown, loose abutment screw, bite imbalance, or soft tissue inflammation. Treatment may range from professional cleaning and antimicrobial care to screw replacement, occlusal adjustment, surgical cleaning, or complete removal of the implant. If removal is necessary, healing may take 8 to 16 weeks for minor defects and 3 to 6 months or more when bone grafting is required. Replacing the implant too soon in a contaminated or unstable site often increases the chance of another failure.
It is wise to get a second opinion if the explanation feels incomplete or if the proposed corrective treatment is costly. A second clinician can review whether the implant was well-positioned, whether the original plan was appropriate, and whether the problem is biological, mechanical, or both. Costs can vary widely. Simple repair of a loose prosthetic component may be a few hundred dollars, while removal, grafting, and replacement can exceed $5,000 to $10,000.
If you suspect negligence, do not alter or discard documents. Ask for itemized bills and written explanations. Some patients also notify their dental insurer, travel insurer, or financing provider if the treatment was performed abroad or through a package clinic. The practical goal is to stabilize your oral health first and sort out responsibility once the medical facts are clear.
Can You Get Compensation for Dental Implant Failure
You may be able to get compensation for dental implant failure, though it depends on why the implant failed and what losses you can prove. Compensation is more likely when the failure was caused by negligence, poor planning, lack of informed consent, avoidable technical error, or a defective product. If the implant failed despite appropriate care and the risk had been properly explained in advance, payment may be limited to warranty terms, goodwill treatment, or insurance coverage rather than legal damages.
Compensation can take several forms. Some clinics offer partial or full replacement of the implant, abutment, or crown under a written guarantee, though these policies often exclude smoking, missed follow-ups, poor hygiene, and untreated bruxism. If a single implant and crown cost $3,000 to $6,500, and corrective work involves removal, grafting, and replacement, total expenses may rise above $8,000 or even $12,000 in complex cases. A compensation claim may seek reimbursement for these direct treatment costs.
In stronger negligence cases, compensation may also include the cost of corrective surgery elsewhere, consultation fees, imaging, medication, lost wages from time off work, travel expenses, and damages for pain or nerve injury. If a patient suffered permanent numbness, chronic sinus problems, severe infection, or major bone loss requiring extensive reconstruction, the value of the claim can increase substantially. The exact amount depends on local law, medical evidence, and the extent of lasting harm.
To pursue compensation, patients usually need records that show what happened and when. Useful documents include treatment plans, invoices, X-rays, CBCT scans, photographs, consent forms, e-mails, post-operative instructions, and evidence of follow-up attendance. An independent expert opinion is often critical because it helps separate an accepted clinical risk from negligent care. If the provider promised a specific result in marketing materials or verbally guaranteed permanence, that may also affect the claim, though advertising language alone is not always decisive.
Some cases resolve through direct negotiation with the clinic, complaint procedures, professional regulators, malpractice insurers, or consumer protection channels. Others require formal legal action. Time limits can apply, and they may start from the date of treatment or from the date the problem was discovered. Patients should also be aware of shared responsibility. If the records show repeated smoking advice was ignored, maintenance visits were missed for years, or hygiene was very poor, compensation may be reduced. The practical strength of a claim comes from clear causation, credible expert support, and well-preserved documentation of both the clinical failure and the financial loss.
How to Prevent Dental Implant Failure
Preventing dental implant failure starts long before the implant is placed. The strongest prevention strategy is careful case selection, precise planning, and disciplined maintenance over the life of the implant. Most implants perform very well when these elements are in place, with long-term survival often reported above 90%. Prevention is not one single step. It is a sequence of decisions that reduce biological and mechanical risk at every stage.
Pre-treatment assessment matters more than many patients realize. The clinician should review medical history, medication use, smoking status, periodontal history, and bite habits such as clenching or grinding. Imaging should match the complexity of the case. A CBCT scan is often useful when bone width, sinus position, or nerve location is uncertain. If active gum disease is present, that should be treated before implant surgery. Patients with poor glycemic control may need medical stabilization before proceeding. Smokers should be told clearly that failure and infection risk are higher, and reducing or stopping tobacco use can improve outcomes.
Surgical planning should focus on bone quality, implant size, insertion stability, and clean technique. If the site lacks adequate bone, grafting may be safer than forcing an implant into a compromised position. During healing, the implant should not be overloaded. In some cases immediate loading works well, but it depends on torque, stability, bone density, and prosthetic design. A rushed loading protocol in a weak site can increase micromovement and disrupt integration.
After placement, home care and professional maintenance become the main defense against late failure. We usually advise patients to brush carefully twice daily, clean around the implant with interdental aids, and attend maintenance visits every 4 to 6 months unless their clinician recommends a different schedule. Those visits allow early detection of plaque retention, bleeding, pocket changes, screw loosening, and bite overload. Patients with bruxism may need a custom night guard to protect the crown and surrounding bone from excessive force.
Diet and habits also play a part. Avoiding hard pressure on the new implant during early healing, following medication instructions, and reporting bleeding, swelling, or bad taste quickly can prevent small complications from becoming larger failures. Good implant prevention is practical and measurable: stable oral hygiene, regular reviews, controlled health risks, and early treatment of inflammation. When those steps are taken seriously, implants often remain functional for 10, 15, or 20 years or longer.
Frequently Asked Questions About Dental Implant Failure
Patients often have very specific questions about dental implant failure because the issue affects health, cost, and trust in treatment. One of the most common questions is whether implant failure means the body “rejected” the implant. True rejection is uncommon. Most failures are caused by infection, poor integration, bone loss, overload, or untreated risk factors rather than an immune reaction to titanium. Another frequent question is how long implants are supposed to last. Many function for 10 to 20 years or longer, and some last several decades, though the crown on top may need maintenance or replacement sooner than the implant fixture itself.
People also ask whether pain always means failure. It does not. Mild discomfort after surgery can be normal for several days. Persistent or worsening pain after the early healing phase deserves review because it may signal infection, instability, or bite-related overload. Patients often want to know whether a failed implant can be replaced. In many cases, yes. The failed implant may be removed, the site cleaned or grafted, and a new implant placed after healing. The delay can range from a few weeks to 6 months or longer depending on infection and bone loss.
Cost is a major concern. If the implant fails, patients ask who pays for the replacement. The answer depends on the cause, the clinic’s guarantee policy, and whether negligence is involved. Some offices replace the fixture at reduced cost but charge again for grafting or a new crown. Others offer more comprehensive warranties if maintenance rules were followed. In many markets, revision treatment can cost nearly as much as the original treatment, and sometimes more because the bone site is less favorable.
Another common question is whether smoking really makes that much difference. Clinically, yes. Heavy smoking can impair blood supply and increase the risk of peri-implantitis and healing complications. Patients also ask if implants can fail years later after feeling normal for a long time. They can. Late failure often relates to hygiene problems, peri-implantitis, bite stress, or loosening parts that were not corrected early. Routine maintenance is one of the most effective ways to spot these issues.
Many readers also ask whether a second opinion is worth it. If the explanation for failure is vague, the proposed repair is expensive, or the trust relationship has broken down, a second opinion is often sensible. Updated imaging and a clear review of records can reveal whether the problem is surgical, restorative, maintenance-related, or a combination of all three. That clarity usually helps patients make better medical and financial decisions.